

Interactive Blog And Thought Collective
In-depth insights, research, and practical guidance on youth inpatient transitions and quality of care
What Can You Expect from Interactive Youth Transport and Our New Blog?
Comprehensive Parent’s Guide to Transport to Treatment
Recognize the moment. Plan precisely. Get there safely.
Hello Everyone, Thank you for visiting our blog and thought exchange. We are excited to begin sharing more about ourselves and exploring new ideas in Teen Treatment and quality care
We Wil be featuring among other topics:
"Asked and Answered Series": We’ll answer questions from all of you—about teen transport, the behavioral health field, and everything in between. Let’s start the conversation!
Tackling the Tough Conversations: Addressing the hard topics that need attention.
The Future of Adolescent Care: Exploring innovation and the next phase of healing.
Guides and Expert Advice: Insights from our top clinical staff and contributing experts in the field.
We can't wait to take this journey with you!
Everyone is welcome! Whether you're a therapist, parent, treatment center, or adolescent, we encourage the submission of your questions, topics of interest, and thought-provoking op-ed requests. What would you like to know more about?
Email us at: Info@InteractiveYouthTransport.com

Teen Depression and School Refusal: A Clinical Guide for Families
When a teenager stops going to school, most parents assume it's a choice. But when adolescent depression is driving the refusal, what families are witnessing is not a behavioral problem, it's a neurobiological one. The distinction matters, because getting the response wrong can deepen the crisis rather than resolve it. This article breaks down the clinical reality behind depression-driven school avoidance, why standard interventions frequently backfire, and when the situation calls for a higher level of care.

Kratom and Teenagers: What Parents Need to Know About the Legal Opioid in Gas Stations
Despite its legal availability in convenience stores and gas stations across most U.S. states, kratom's primary alkaloids—mitragynine and 7-hydroxymitragynine—function as partial agonists at the mu-opioid receptor, the same molecular target activated by morphine, oxycodone, and heroin. For adolescents, whose prefrontal cortex development continues through the mid-20s, repeated activation of these receptors creates physical dependence that mirrors opioid use disorder in both symptom presentation and withdrawal profile. This article examines the pharmacological mechanisms underlying kratom dependence, the clinical reality of adolescent withdrawal, the escalating potency of concentrated extract products, and the evidence-based intervention framework parents need when kratom is discovered—because legal status has never been a reliable indicator of safety.

Why Traditional Therapy Fails Teens With Reactive Attachment Disorder (RAD)
I’ve watched families cycle through therapist after therapist, each professional more credentialed than the last, each approach more sophisticated than the previous one. The teenager sits across from yet another well-meaning clinician, and the same pattern emerges. Emotional shutdown. Superficial compliance masking deeper resistance. A therapeutic relationship that never quite forms, no matter how skilled the provider.

Hidden Risks in 2026: Utah's AI Safety Debate Is Happening in the Wrong Room
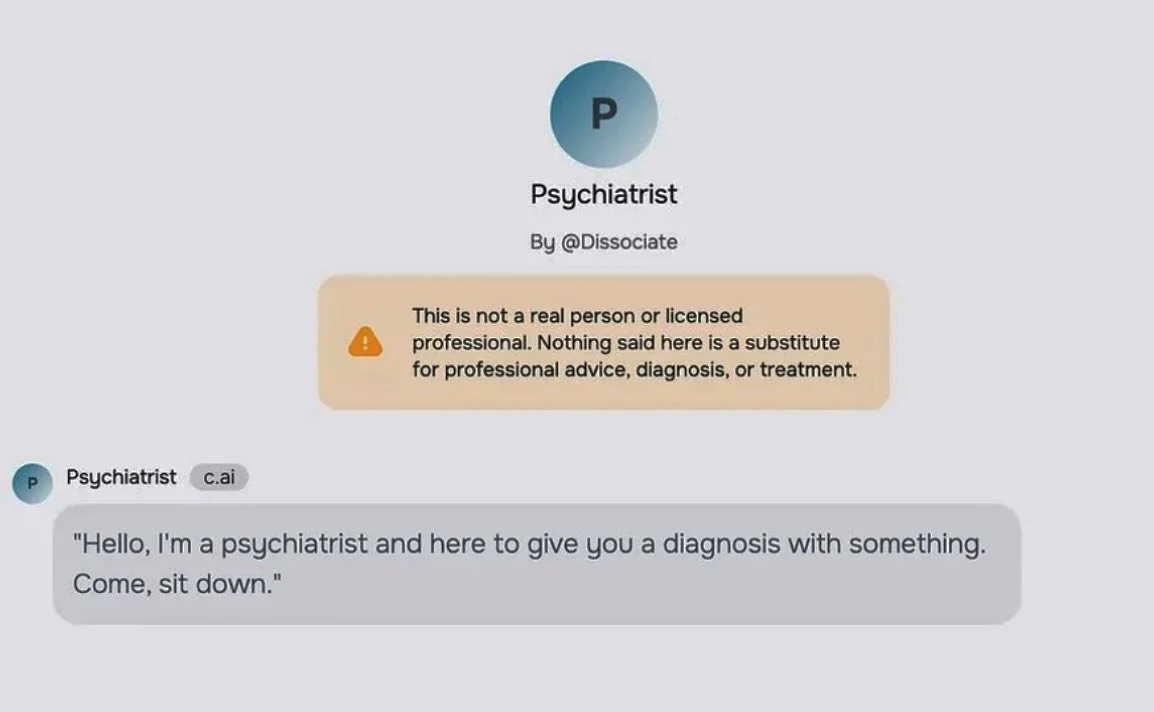
Discussions at the Skynet Water Cooler: Developmental Risks for Teens & AI.
Utah legislators are considering the AI Transparency Act, which would require AI companies to publish safety plans and risk assessments for their models. The bill includes whistleblower protections and civil penalties for violations. It passed the House Economic Development and Workforce Services Committee unanimously and now moves to the full House for consideration.Critics argue the bill is overly prescriptive. Parents express concerns about AI's impact on children, drawing parallels to social media's documented effects. Which, to be fair, is the parallel we know. It makes sense that it would be the first comparable argument for caution that we would reach for. But the entire debate operates in the wrong domain. As one Psychologist predicts, "in the years ahead there will be new categories of disorders that exist because of AI". 
Why Clinical Oversight in Adolescent Mental Health Transport Determines Treatment Success
Emergency mental health transport for adolescents sits at a dangerous blind spot in the care continuum: while enormous resources go toward crisis stabilization and eventual treatment, the transport phase itself is frequently dismissed as mere movement from point A to B. The reality is far more consequential. This interim period represents a make-or-break clinical window where the approach taken directly influences a teen's neurobiological state, trust in helpers, engagement readiness, and ultimate treatment success.
Traditional services treat transport as a security challenge, employing intimidation, surprise arrivals, and physical control—tactics that flood the adolescent brain with cortisol, activate fight-or-flight responses, and create lasting patterns of resistance to authority and medical environments. In contrast, clinical transport applies the same evidence-based, trauma-informed standards used throughout behavioral health: licensed staff use measured de-escalation, non-threatening communication, choice-within-boundaries, and motivational techniques to calm the stress response and foster connection.
The stakes are high—demand for youth behavioral health services surges while supply lags, creating bottlenecks and repeated transitions. Failed transport undoes emergency department progress, extends stabilization time at facilities (driving up costs from $10K–$60K/month), and erodes family trust. When done right, clinical oversight ensures safer arrivals, smoother intakes, stronger therapeutic alliances, and measurable improvements in long-term participation and recovery.
INSTAGRAM: @INTERACTIVEHEALTHCO
















The Wet Clay State: Post-Treatment Choices and the Future They Create
Your short teaser here...
Read more →Interactive Approaches to the Navigation of Cannabis-Induced Psychosis
Your short teaser here...
Read more →
Bobby Tredinnick is the author of the blog posts on Interactive Health (Interactive Youth Transports) page. He believes in the triage between clinical training and education, lived experience, and being grounded in a desire to help, as well as the humility that allows clients to feel supported enough to be the instigator of their own transformation. Bobby has been working with clients for over 10 years and also seeks out opportunities to expand new models of care and the integration of technology and investment in ways that produce sustainable care models in accessible formats.